Book Appointment Now

Sciatica vs Piriformis Syndrome: What’s the Difference and What Actually Helps?
Is it disc-related sciatica or piriformis syndrome? Learn how Pickering and Milton physios tell them apart by pain location, tests, and what treats each.
Sciatica vs. Piriformis Syndrome: What’s the Difference and What Actually Helps?
- Key takeaways
- Sciatica is nerve pain from a problem at the spine (usually a disc), while piriformis syndrome is the same nerve irritated by a muscle deep in the buttock.
- Location of the pain tells you a lot: back-first symptoms point to the spine, buttock-first symptoms point to the piriformis.
- Most sciatica settles in 4 to 6 weeks with conservative care; piriformis syndrome often eases within 1 to 3 weeks of starting targeted exercises.
- Both respond well to physiotherapy. Surgery is rarely the answer for either.
- See a clinician promptly for red flags: new leg weakness, numbness in the groin, or bladder or bowel changes.
If your pain shoots from your low back or butt down the back of your leg, you probably searched “sciatica.” But sciatica is a symptom, not a diagnosis, and one common source is a muscle, not a disc. Knowing whether your pain starts in your back or deep in your buttock changes what treatment works, and it is the first thing a physiotherapist will test.
What sciatica actually means
The sciatic nerve is the largest nerve in the body. It is made up of nerve roots from L4 to S3, runs from the lower spine through the buttock and down the back of the leg, and can be up to 2 cm wide at its thickest point (Davis, Taqi & Vasudevan, StatPearls, updated January 2024). True sciatica means that nerve or one of its roots is being pinched or inflamed at or near the spine. The usual culprits:
- Herniated (bulging) disc pressing on a nerve root. This is the most common cause.
- Spinal stenosis (narrowing of the spinal canal), more typical after age 50.
- Degenerative disc disease.
- Less commonly, spondylolisthesis or a pelvic or spinal mass.
The pain is usually one-sided and travels below the knee. Coughing, sneezing or bending forward often makes it spike, because those movements raise pressure around the disc.
What piriformis syndrome is
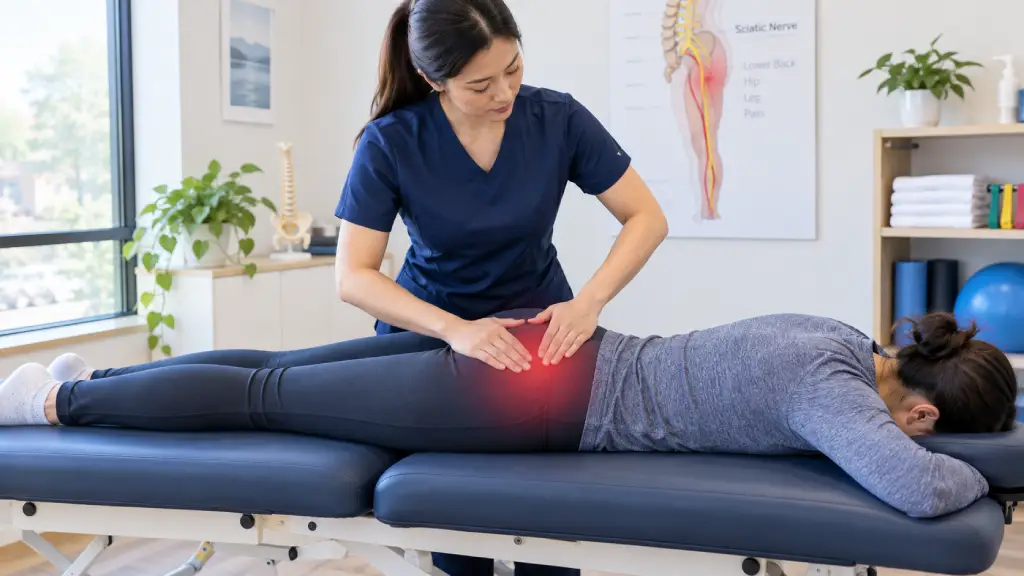
The piriformis is a small, deep muscle in the buttock that helps rotate the hip outward. The sciatic nerve runs right next to it, and in some people passes through it. When the muscle gets tight, spasmed or inflamed, it irritates the nerve and produces pain that feels almost identical to disc-related sciatica: shooting, burning or aching down the back of one leg, often with numbness or tingling (Hicks, Lam & Varacallo, StatPearls, updated August 2023).
Classic triggers are prolonged sitting (office work, long drives, cycling), a hard fall on the buttock, and sudden increases in hip-dominant training. It shows up in people who sit for hours: taxi and rideshare drivers, cyclists, runners. Estimates suggest it accounts for roughly 0.3% to 6% of low back and sciatica-type pain cases, and it is far more commonly reported in women than men (about 1:6). A 2024 study in the British Journal of Pain (Yürük) found prevalence estimates from 5% to 36% depending on how strictly doctors define it, which is why a hands-on exam matters more than any single test.
Sciatica vs. piriformis syndrome: quick comparison
| Feature | Disc-related sciatica | Piriformis syndrome |
|---|---|---|
| Where pain starts | Low back, then down the leg | Deep buttock, then down the leg |
| Worse when | Coughing, sneezing, bending forward | Sitting for 15-30+ minutes, climbing stairs |
| Better when | Standing, gentle walking (for many) | Standing, walking, lying on the unaffected side |
| Numbness pattern | Specific strip of leg/foot (follows a nerve root) | Mainly buttock, posterior thigh, sometimes foot |
| Key exam clue | Positive straight-leg raise from the back | Pain reproduced by stretching the piriformis (FAIR test) |
| Imaging | MRI may show disc pressing a nerve root | X-rays and MRI usually look normal; diagnosis is clinical |
| Typical timeline | 4-6 weeks with conservative care | 1-3 weeks after starting a good exercise program |
The table is a guide, not a verdict. The two can also coexist, and other conditions, like hip joint arthritis or sacroiliac joint dysfunction, can mimic both. That is why a proper assessment is worth booking before you self-treat for weeks.
How a physiotherapist tells them apart
There is no blood test or single scan for either condition, so the diagnosis comes from your history and the physical exam. In a typical assessment we will:
- Map your symptoms: where the pain starts, how far it travels, what makes it better or worse.
- Test nerve tension: a straight-leg raise reproduces disc-related nerve pain; the FAIR test (hip flexion, adduction and internal rotation) reproduces piriformis pain.
- Palpate the buttock: tender spot over the sciatic notch with pain on pressure suggests the muscle.
- Check your back, hip and SI joint range of motion and strength.
- Screen for red flags (progressive weakness, saddle numbness, bladder or bowel changes) and refer for imaging or medical review if anything looks concerning.
If pain has persisted 6 to 8 weeks without improving, or there are neurological deficits, guidelines support MRI; StatPearls notes imaging is otherwise of little initial value.
Treatment that works for both
The encouraging news: most people recover without surgery.
For disc-related sciatica. Keep moving; prolonged bed rest makes it worse. Most cases settle in under 4 to 6 weeks even without treatment, per StatPearls (2024). Physiotherapy speeds this with directional preference exercises, nerve glides, manual therapy and gradual loading. The American Medical Association’s What Doctors Want Patients to Know guidance (Dr. Kevin Taliaferro, Henry Ford Health, accessed September 2026) emphasizes staying active and seeking care for atypical symptoms like leg weakness or bowel or bladder changes. Surgery is reserved for persistent, severe or progressive cases.
For piriformis syndrome. Short rest (no more than 48 hours), then targeted stretching, hip and core strengthening, soft-tissue work and activity modification. StatPearls reports most people become symptom-free within 1 to 3 weeks of starting an exercise program, but relapse is common when people stop doing the exercises. Deep-tissue massage and myofascial release can reduce muscle spasm around the nerve; see our guide on how massage therapy may help sciatica. Injections are an option when conservative care stalls.
A numbered starter plan while you wait for your appointment:
- Take standing or walking breaks every 30 to 45 minutes; do not sit through a full workday.
- Ice the buttock 15 minutes on, 1 hour off for the first 48 hours if the pain is sharp and new.
- Do gentle pain-free stretches twice daily: knee-to-chest, figure-four piriformis stretch and hamstring stretches.
- Sleep on your side with a pillow between your knees.
- Book an assessment if pain shoots below the knee, lasts beyond a couple of weeks, or you notice weakness or numbness.
When to get help urgently
Go to an emergency department the same day if you have loss of bladder or bowel control, numbness around your groin or inner thighs, or rapidly worsening leg weakness. These can signal cauda equina compression, a rare but serious cause of sciatica-like pain. Otherwise, a physiotherapist can usually identify the source in one or two visits and start treatment right away.
Living and working in the Pickering and Milton, Ontario
Prolonged commuting on the 401 or 410, desk jobs in Pickering’s and Milton’s office parks and fall training blocks all stack the same load onto the lower back and buttocks. If you have been white-knuckling leg pain through the workweek, get it looked at. Our physiotherapists and registered massage therapists in Pickering and Milton, Ontario assess nerve-related leg pain every week and build recovery plans around your actual schedule.
- Book an appointment online at our Pickering or Milton clinic.
- Contact us to ask about direct billing or WSIB coverage.
- Related read: Physiotherapy for plantar fasciitis, another overuse pain that gets better with the right loading plan.
Frequently asked questions
How long does sciatica take to heal?
Most cases improve in 4 to 6 weeks with conservative care, and many resolve fully in that window according to StatPearls (2024). If pain still radiates below the knee after 6 to 8 weeks despite treatment, that is the usual point to discuss imaging with your clinician.
Is piriformis syndrome the same as sciatica?
No. Piriformis syndrome irritates the sciatic nerve in the buttock, while classic sciatica means the nerve is compressed near the spine, usually by a disc. Both produce sciatic nerve pain, which is why they get confused. The starting location of your pain is the big clue.
Does walking help sciatica or piriformis syndrome?
For most people, yes. Gentle walking keeps the nerve moving, reduces stiffness and is better than bed rest for disc-related sciatica. For piriformis syndrome, walking breaks up the sitting position that aggravates the muscle. Stop and get assessed if walking rapidly worsens numbness or weakness.
What does the physical exam involve for leg pain?
Expect movement tests (straight-leg raise, FAIR stretch), strength and reflex checks, palpation of the buttock and spine, and red-flag screening. Imaging is not routine at first; MRI is reserved for deficits or pain that does not settle, per StatPearls.
Can massage therapy help sciatic nerve pain?
Massage cannot un-pinch a disc, but it can ease the muscle spasm around an irritated sciatic nerve, which is why StatPearls lists deep-tissue massage as part of piriformis syndrome management. Book it alongside physiotherapy rather than instead of it, especially if you have numbness or weakness.